The operating system for your clinic and pharmacy
One record, from the front desk to the dispensary to the claim. The consultation, what was dispensed, what was paid and what is claimed are the same visit, not four systems that have to be reconciled afterwards.
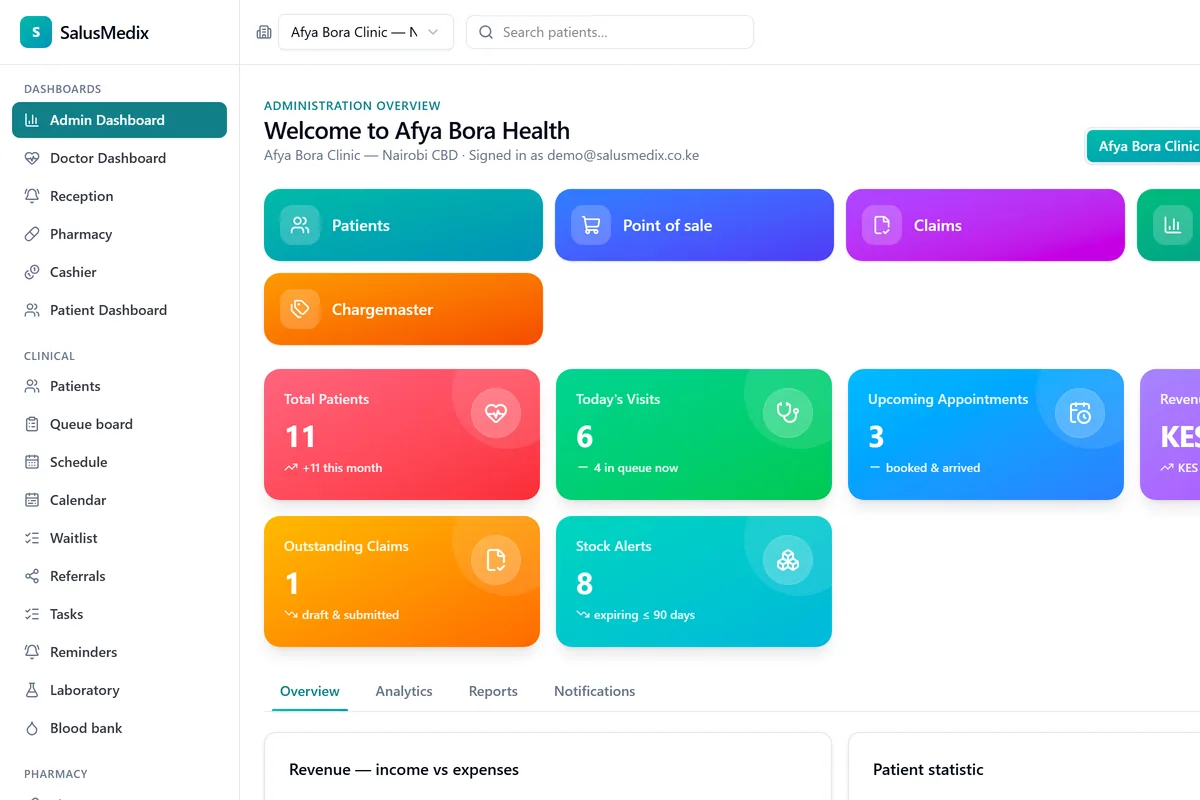
The demo runs on invented data with integrations simulated. Nothing in it is real. Full product at salusmedix.co.ke.
Where the record breaks
Every one of these is a gap between two systems that were supposed to agree.
The dispensary has a different record
The clinician wrote the prescription in a book. The dispensary keyed it into the POS. By month end the two disagree about what was given, and nobody can say which is right.
Six boxes expired on the shelf
They were behind newer stock that arrived later and got dispensed first. Nobody was counting expiry dates, only quantities.
The M-Pesa statement and the day's takings differ by 4,200
Somewhere between the till, three phones and a paper receipt book, a payment went in twice or not at all. Finding it takes an afternoon.
The claim came back rejected
A coding error made at the consultation, discovered six weeks later by someone who was not there. The visit has to be reconstructed from memory.
The second branch runs differently
You opened another location and it invented its own way of doing things. Comparing the two means exporting from both and hoping the columns line up.
The patient came back and nobody knew
Same patient, three months later, different clinician. The last visit is in a file somewhere, so the history gets taken again from scratch.
What it does
OPD and EMR on one patient record
Appointments, consultation notes, ICD-11 coding, lab and imaging requests, maternity and MCH. The record follows the patient across branches rather than sitting in one building.
Pharmacy and POS that dispense first-expiry-first
Stock is issued in expiry order automatically, so the boxes at the back cannot quietly go out of date behind newer deliveries.
M-Pesa at checkout, eTIMS on the invoice
Payment is taken against the visit, and the tax invoice is issued from the same transaction. The day's takings and the M-Pesa statement are the same list.
The claim is built from the visit
Not re-typed from it. The diagnosis, the coding and the items dispensed are already there when the claim is assembled, which is where most rejections come from.
Several branches, one view
A clinic with a dispensary, a standalone chemist and a larger medical centre can run side by side, each the way it actually works, with a group view across all of them.
An audit trail nobody can rewrite
Append-only, with multi-factor sign-in and data isolation between facilities. Built for the questions an inspection asks, not the ones a demo asks.
What is not switched on yet
Read this before you buy, not after.
SHA claims: built, certification in progress
The claim pipeline, the FHIR bundle and the submission outbox are built and testable today. Live submission to SHA is gated on DHA HMIS certification, which is a vendor onboarding process rather than a coding task. If you need SHA billing switched on from day one, talk to us before you buy.
Cash-first is what ships today
M-Pesa, eTIMS and SMS run on live credentials. Everything else in the clinical, pharmacy, billing and inpatient surface is working. We would rather you knew which half is gated than discovered it in month two.
Per branch. Not per user.
Adding a clinician, a locum or a intern does not change the bill, and we take no share of what you dispense.
Essential
A clinic or chemist getting one record in place.
Standard
The full clinical, pharmacy and billing surface.
Pay annually and two months are free.
No revenue share, and no per-user fee.
Questions
Open the demo before you book anything
A fictional three-branch group, loaded and running. Fifteen minutes will tell you more than a call.